How to Switch From Allergy Shots to At-Home Sublingual Immunotherapy
Make the switch when your allergen profile matches an approved tablet and asthma is controlled.

Switching from allergy shots to at-home sublingual immunotherapy, or SLIT, can be a manageable change when a physician confirms that the treatment fits your allergens and health history. The switch calls for a plan to stop shots, a first SLIT dose under supervision, and daily treatment at home. The key is to change the delivery route without abandoning the long-term goal of building immune tolerance.
Why patients on allergy shots consider switching — and what makes the question worth taking seriously
Consider a patient who has been getting allergy shots for a year. Symptoms are more manageable, but every appointment has become something to dread. The treatment works. The schedule does not. Frequent visits, travel, and the observation period after each injection can make a multi-year course hard to finish, even for someone who wants the benefits.
That tension is a legitimate reason to discuss another route. Subcutaneous immunotherapy, or SCIT, requires medical supervision because injections can cause systemic reactions, so the office commitment is part of its safety structure. SLIT moves ongoing dosing home after supervised initiation, changing how treatment fits into daily life. An allergy organization’s 2026 Position Paper recognizes SLIT as an established form of allergen immunotherapy with demonstrated efficacy and a favorable safety profile.
What SLIT actually does in the body and why it qualifies as disease modification, not symptom masking
SLIT exposes the immune system to an allergen through the tissues under the tongue. A tablet dissolves there, or prescribed liquid drops are placed there, allowing mucosal immune cells to encounter the allergen. As exposure repeats over time, the immune response shifts from reactivity toward tolerance. Shots pursue the same immune endpoint through injections. The route changes, but the underlying aim does not.
This differs from relieving symptoms after an allergic response has begun. Antihistamines block histamine, while other symptom treatments dampen inflammation. Allergen immunotherapy is the only potentially disease-modifying treatment for IgE-mediated respiratory allergy because it targets the immune response itself. “Potentially” is an important qualification, though. It describes what a completed course can achieve, with individual responses varying.
What evidence separates that promise from temporary relief? Randomized trials of grass and house dust mite SLIT show clinically meaningful reductions in symptoms and medication use, with benefits observed up to one to two years after a three-year course. Real-world cohorts also report fewer new cases of asthma and less medication dispensed over the long term after SLIT, though these findings cannot show how any one patient will do.
How SLIT and allergy shots compare on effectiveness, safety, and day-to-day logistics
For allergic rhinitis, SLIT and shots help with symptoms and reduce medication use to much the same degree, and neither route works better across the board. That does not make every formulation interchangeable. A treatment still needs to cover the allergens driving a patient’s symptoms, and its benefits depend on sustained use.
Safety changes where dosing can happen. Shots can cause systemic reactions, which explains the medical supervision and post-injection observation. SLIT reactions are predominantly local, including oral itching, throat irritation, and mild mouth swelling, and they usually diminish with continued dosing. Serious systemic reactions remain possible with SLIT. Its favorable safety profile allows treatment at home after the first supervised dose, with precautions still in place.
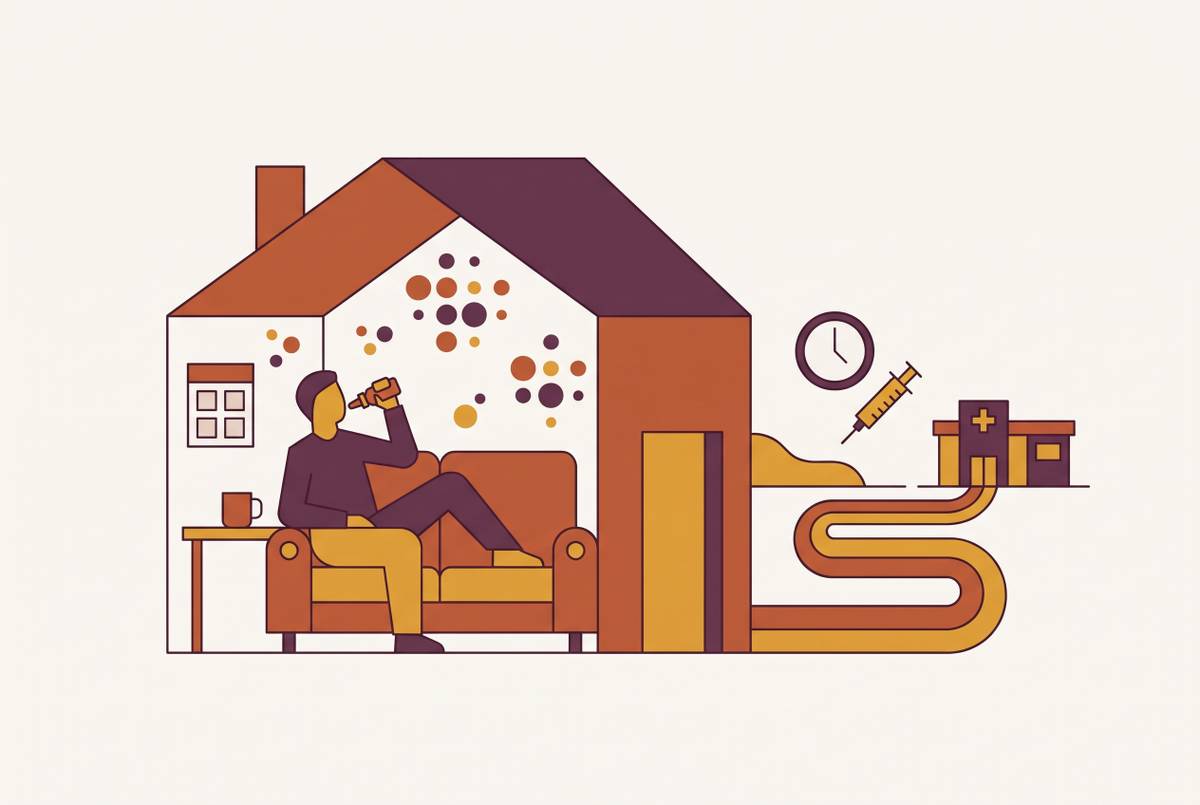
The difference in time commitment is substantial. Shots call for frequent visits during build-up, then maintenance injections every two to four weeks for years, and patients must be watched after each dose. SLIT replaces that recurring clinic schedule with daily dosing at home. In the U.S., liquid SLIT drops are off-label, though they are taken under the tongue in the same way.
Approved tablets have narrower allergen coverage than some patients need. The four FDA-approved products are Odactra for house dust mite, Grastek for Timothy grass, Oralair for a 5-grass mix, and Ragwitek for short ragweed. As of 2025, all four have indications for ages 5–65. There is no approved tablet for cat, dog, or less-common molds. Patients whose symptoms come from those allergens may need to stay on shots or talk about off-label drops directed by a physician.
Who is and isn't a good candidate to switch
Convenience alone cannot establish whether SLIT is appropriate. A good candidate may have confirmed IgE-mediated allergic rhinitis, with or without mild controlled asthma, and sensitivity to house dust mite, grass pollen, or ragweed. Someone who follows a shot protocol reliably but cannot sustain the clinic schedule has a clear practical reason to consider switching. Even then, physician evaluation determines eligibility.
All four FDA-approved tablet labels contraindicate treatment in patients with severe or uncontrolled asthma and in those with a history of eosinophilic esophagitis, or EoE. If a patient has had severe systemic or severe local reactions to SLIT or has hypersensitivity to product excipients, the physician must also check the label for that product. Preference does not override these restrictions.
Allergen mismatch is another barrier, separate from safety. A patient whose main triggers are cat, dog, cockroach, or many tree species cannot replace that coverage with an on-label tablet for an unrelated allergen. Off-label drops may offer an option, but only after a physician evaluates the fit. Children who have been on shots may also be candidates, since tablet indications extend down to age 5. Their age alone does not settle the other clinical questions.
Can I stop allergy shots and switch to sublingual drops at home instead?
The first step is a conversation with the prescribing physician. Stopping shots without a plan for what comes next can break the planned course of immune exposure. The physician needs to know whether treatment is still in build-up or has reached maintenance, because that affects the handoff. When a patient asks to switch, the physician can also discuss whether tablets or off-label drops are a better match for the confirmed allergens.
Several questions make that discussion concrete. Does an approved tablet cover the allergens responsible for your symptoms, or would drops require consideration? If asthma is present, is it controlled well enough for SLIT? Does the current stage of SCIT affect when shots should stop? The patient should also establish who will manage the transition, whether that is the current allergist, a referred physician, or a telehealth-based allergy physician.
The evaluation usually draws on prior skin-prick or specific IgE testing to review the sensitization profile. If those results are outdated or insufficient, a physician-ordered or physician-reviewed at-home finger-prick IgE test may help refresh it. Clinical oversight distinguishes that process from buying an over-the-counter sensitivity kit and interpreting it alone. During a telehealth consultation, a physician can go over the patient’s history, test results, and medications they now take. However, a virtual evaluation does not remove the requirement for supervised tablet initiation.
How the transition is structured — what stops, what starts, and in what order
First, the physician coordinates the end of shots. Patients should not stop during build-up without guidance, while those in maintenance may have more flexibility in scheduling the change. A short washout or bridging period may be used if the physician considers it appropriate. The physician determines the exact gap, as this guidance supplies no universal interval.
Next, the physician finalizes the formulation and allergen coverage discussed during evaluation. That may be an approved tablet or an off-label liquid preparation. For patients with several relevant allergens, drops can allow combinations beyond those available in individual tablets, with each combination requiring evaluation for appropriateness. The prescription needs to reflect the patient’s confirmed sensitizations.
Before home dosing begins, the first tablet dose must be taken under experienced medical supervision. All four FDA-approved tablet labels require patients to be watched for thirty-minute observation and have epinephrine available. Initiation may take place in a physician’s office, allergy clinic, or an appropriate affiliated facility used by a telehealth provider, depending on the product and local practice. Drops also begin with a supervised dose under the physician-directed protocol.
The prescriber must also prescribe an epinephrine auto-injector and train the patient in its use for SLIT tablet therapy. Patients should have it before they start taking doses at home. After supervised initiation without a significant reaction, treatment continues at home with one tablet or the prescribed drop dose daily. “At home” tablet dosing requires patients to keep epinephrine on hand for as long as they take the tablets.
Grastek and Ragwitek specify starting before the relevant pollen season, while Oralair specifies at least four months before the expected grass pollen season. Odactra treats a year-round allergen. If a patient asks to switch mid-season, they may need to wait for the next pre-season window to start a seasonal tablet. A non-seasonal option is relevant only if it addresses an allergen the patient actually needs treated.
What to expect in the first weeks and months after switching
Early doses may cause oral itching, tingling, mild throat irritation, or mild mouth swelling. These local effects commonly lessen within the first few weeks as treatment continues. They can be uncomfortable without indicating a systemic reaction. Still, “expected” does not mean every reaction should be ignored. The prescribing physician should be contacted for effects beyond mild local symptoms.
Difficulty swallowing, throat tightening, chest symptoms, or hives after a dose warrant immediate medical attention. If severe systemic symptoms occur, use the epinephrine auto-injector and get emergency care. Do not wait for a routine follow-up appointment. Although SLIT’s reactions are usually local, its rare systemic risks are the reason emergency preparation remains necessary.
The other adjustment is the pace of improvement. Immune adaptation happens over months and years, and the absence of a dramatic early change can make patients question whether treatment is working. Some notice improvement within the first season. That early response is different from completing the course needed for durable benefit. Missed doses do not restart the clock, but inconsistent dosing can slow immune adaptation, so day-to-day use remains clinically important after the clinic visits end.
How to sustain the treatment long enough for it to work
The WAO paper recommends prescribing SLIT for at least three years to pursue sustained, disease-modifying benefit. Feeling better early does not show that the planned course is complete, and slow improvement at first does not by itself show that treatment has failed. Consistency needs to be planned for from the outset. Removing appointments solves one adherence problem but leaves the daily dose to remember.
A fixed routine can make that task easier. Taking the prescribed dose at the same time and in the same place connects treatment to an ordinary part of the day. Keeping medication in the same place where it is easy to see, and planning to bring it on trips, can help patients avoid missing doses. Home treatment no longer depends on proximity to the injection clinic. Its flexibility is most useful when the routine travels with the patient.
Cost also belongs in the initial plan. Physician-ordered SLIT may be covered with FSA or HSA funds where applicable, which can help reduce the financial pressure to discontinue. That does not make treatment cost-free. Discussing eligible expenses before starting gives the patient a clearer view of the commitment rather than discovering a barrier after the transition.
Ongoing care remains part of home treatment. At check-ins once or twice a year, the prescribing physician can see how treatment is working, review new sensitizations, and keep a record of progress. Telehealth can make those visits easier by removing travel and waiting-room time. The aim is not to replace medical care with self-management, but to put daily dosing where it is easier to sustain while keeping clinical decisions with the physician.
Sources
- Efficacy and safety of sublingual immunotherapy for allergic rhinitis: A network meta-analysis
- World Allergy Organization Sublingual Immunotherapy Position Paper: 2026 update - World Allergy Organization Journal
- Sublingual Immunotherapy (SLIT): Treatment & Results
- Critical appraisal of the clinical utility of sublingual immunotherapy in allergy