Why Indoor Allergen Loads Make the Case for Switching From Shots to Sublingual Drops
Year-round indoor allergens make the case for switching to at-home sublingual drops.

At-home sublingual immunotherapy can be an alternative for adults who want to switch from allergy shots, with a physician guiding the change and a supervised first dose. Persistent indoor allergens make the case for treatment that retrains the immune response and fits daily life. Sublingual drops offer that practical advantage, although evidence does not establish that every drop formulation matches shots for every allergen.
Why indoor allergens don't follow a season
Dust mites, pet dander, mold, and cockroach debris are persistent features of indoor environments. Unlike outdoor allergens that arrive in pulses, these triggers can remain where people sleep, sit, and spend their days. Their presence makes the familiar idea of an “allergy season” a poor description of indoor exposure.
Dust mite triggers include proteins in fecal particles and shed skin, which become airborne during bed-making or vacuuming. Pet allergens come from proteins in saliva, dander, and urine, so no hypoallergenic breed removes the source. Dander can stay airborne for hours and lodge in fabrics, carpets, and walls, persisting long after an animal leaves. Mold is another lasting source of allergens where the air indoors is damp enough for it to grow. There is no dependable calendar date when this load disappears.
How constant exposure drives sensitization at population scale
A large majority of Americans encounter dust mite allergens, and a substantial share of homes contain enough to trigger reactions in susceptible people. Dust mite sensitization is the most prevalent indoor allergen sensitization. Pet dander exposure also reaches a majority of the population, yet people living with animals do not always connect their symptoms to that exposure.
Exposure and sensitization are not the same thing. Being around an allergen does not, by itself, establish that someone is allergic to it. But enough dust mite exposure can help cause new sensitization as well as keep an existing allergy going.
Mold symptoms are frequently mistaken for something else, leaving mold sensitization underrecognized. Pet owners may also live with symptoms that keep coming back without realizing that the animal plays a part. With so many people exposed and some unaware of their triggers, the problem reaches beyond those already seeking allergy treatment. A useful treatment model therefore needs to make identification accessible.
What continuous exposure does to the body beyond a runny nose
Congestion that lasts can force people to breathe through their mouths, even while they sleep. Mouth breathing changes muscle mechanics, worsens snoring, and can aggravate sleep-disordered breathing in people already predisposed to it. The consequences can extend into the next day. Disrupted sleep can contribute to brain fog, weaker memory, and impaired focus that a person may accept as their normal baseline.
Some symptom remedies can complicate that picture. First-generation antihistamines such as diphenhydramine cross the blood-brain barrier and block histamine receptors involved in alertness. They also inhibit acetylcholine, a neurotransmitter important for memory and focus. Diphenhydramine cuts down on REM sleep, which helps with memory and mood, so sleeping longer may not leave a person better rested.
Second-generation antihistamines have fewer cognitive side effects, but they still treat symptoms. Symptom relief has a useful role. The limitation is that indoor exposure supplies no predictable season’s end at which the underlying problem recedes. For someone repeatedly treating congestion, poor sleep, and reduced focus, the question becomes whether relief alone is enough.
Why allergen immunotherapy is the only intervention that changes the underlying problem
Allergen immunotherapy is the only potentially disease-modifying treatment category for IgE-mediated respiratory allergy. Its aim differs from symptom suppression. Rather than only interrupting an allergic reaction, it works toward changing how the immune system responds to the trigger. Both allergy shots and sublingual immunotherapy belong to this category, so the argument for immune retraining does not automatically settle which route is preferable.
Sublingual immunotherapy, or SLIT, places allergen extract under the tongue. The oral mucosa, the lining of the mouth, supports the development of allergen-specific tolerance. In everyday terms, treatment attempts to teach the immune system not to treat that allergen as a threat. This process takes sustained treatment. Antihistamines and nasal sprays do not provide the same retraining.
The WAO 2026 Position Paper gives the evidence for how well house dust mite SLIT works its highest rating, with nearly all experts in agreement. Evidence suggests SLIT may reduce the risk of new asthma onset, including after treatment stops. That possibility explains why disease modification is a different goal from getting through another congested day.
Can I switch from allergy shots to drops at home when clinic visits become the obstacle?
Allergy shots, also called subcutaneous immunotherapy or SCIT, require repeated injections under medical supervision. Patients are watched after each injection because systemic reactions are known risks, including anaphylaxis, which is rare but can be life-threatening. The supervision serves a clinical purpose. It also means that treatment depends on returning to a clinic throughout a multi-year course.
Every dose therefore takes time to travel, wait, and arrange a visit. For someone who faces indoor exposure all the time, a weekly or biweekly appointment adds another task that keeps coming around. Shots can treat year-round allergies, but sustaining treatment over years can become difficult when participation repeatedly means leaving home or work.
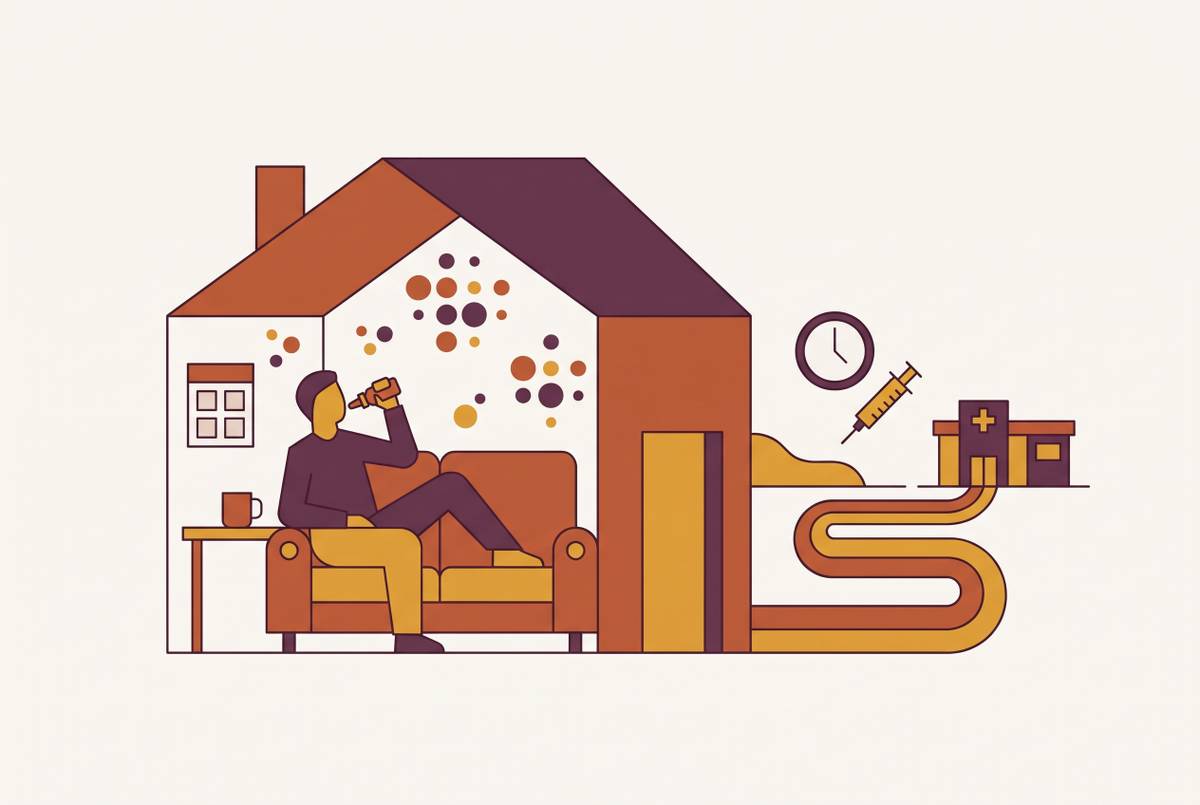
For adults considering a switch, that distinction is essential. At-home drops merit discussion with a physician because a home-based route may fit more reliably into daily life. A physician-guided change can address that delivery burden without abandoning the goal of immune retraining.
What the head-to-head evidence actually shows between shots and drops
Do shots work better despite the trouble of getting them? Seven direct-comparison randomized controlled trials present a mixed picture. Several found that symptoms and medication use fell by about the same amount, while others suggested that SCIT worked better on some measures. Some meta-analyses also favor shots for certain seasonal allergic rhinitis outcomes. The evidence does not support blanket equivalence across allergens, formulations, and measures.
An adjusted indirect comparison using the Rhinoconjunctivitis Quality of Life Questionnaire found no significant difference between SCIT and SLIT. The same analysis found a cost advantage for SLIT per successful outcome. Those findings support considering delivery and cost in the decision, but an indirect comparison is not interchangeable with a direct trial. Evidence for SLIT as a whole also does not show that every personalized drop mixture works equally well.
Adherence is the next part of the comparison. A treatment’s potential benefit cannot be fully realized if the patient abandons it. A large telemedicine cohort reported strong self-reported adherence to the minimum dosing threshold and low discontinuation, supporting the practicality of home treatment without proving that it outperforms shots. SLIT also has a lower anaphylaxis risk than SCIT, which helps make home administration appropriate after a supervised first dose.
Why sublingual drops specifically suit indoor allergens better than tablets
FDA-approved SLIT tablets address single-allergen indications, including grass, ragweed, and dust mite allergy. Grastek addresses Timothy grass, while Oralair addresses a 5-grass mix. A dust mite tablet therefore does not also address pet dander or mold.
Personalized drops can be compounded to include multiple allergens. That flexibility makes them a potential fit for someone sensitized to both dust mites and pet dander, or to mold as well. But flexibility is not proof of equal effectiveness for every mixture. The regulatory distinction also remains important, because the regulator-approved tablets described here are not interchangeable with compounded drops. Formulation, adequate dosing, and convenience belong in the clinical decision.
Chet Tharpe and colleagues’ June 2026 retrospective telemedicine cohort study found clinically meaningful improvement in roughly a quarter of patients at 12 months and nearly half at 24 months. Medication use declined over time. Quality-of-life improvement also grew with treatment duration, reaching the vast majority by 30–36 months. These observational findings support the promise of personalized treatment, while leaving the limitations of a nonrandomized comparison intact.
A separate 5-year real-world house dust mite SLIT surveillance study found that benefit persisted after a 3-year treatment course ended. Symptoms rebounded in the control group but not in the SLIT group. That finding supports durability for the treatment studied, rather than proving the same result for every multi-allergen formulation. Optimal benefit depends on adequately dosed, standardized formulations and sustained adherence for at least three years.
How at-home testing and telehealth remove the access barriers that have kept most indoor allergy sufferers untreated
A person who reacts to mold and pet dander needs a plan for those triggers rather than one that assumes dust mites cause every indoor symptom. At-home finger-prick testing, with a physician who interprets the results, can show specific IgE sensitization without a clinic visit. Testing is particularly useful when symptoms are severe, triggers are unclear, or immunotherapy is under consideration. The interpretation connects the result to the treatment decision.
Telehealth can also shorten the route to that discussion. Seeing a new allergist may mean waiting weeks to months, while telehealth platforms usually have same-week or next-week appointments. The same model can connect testing, consultation, and prescribed home treatment. That reduces entry friction as well as the recurring travel burden. It does not remove the need for medical oversight.
Cost still deserves a concrete comparison. Telehealth allergy consultations, allergy blood testing, prescribed medications, and sublingual immunotherapy qualify as eligible medical expenses under FSA and HSA rules. That can make out-of-pocket spending more manageable for eligible patients. Monthly plans with a fee for the first consultation also handle payment differently from years of in-office treatment, but a low advertised monthly rate alone does not show which costs less in total. Someone thinking of switching needs to weigh both what they can afford and whether they can keep up with treatment.
The case for starting immune retraining now rather than managing symptoms indefinitely
Indoor exposure has no season when it can be counted on to end. That does not mean every month of delay inevitably causes new disease, or that every person with indoor symptoms needs immunotherapy. It means the decision should account for repeated congestion, disrupted sleep, medication use, and the practical burden of continuing the same approach. When those costs persist, reassessing the plan is reasonable.
The evidence also gives that decision a time horizon. In the telemedicine cohort, improvement was greater at 24 months than at 12 months, while durable benefit in the house dust mite surveillance study followed a full treatment course. Immune retraining is a long-term choice alongside symptom relief. Its potential to alter the course of allergy requires time to yield benefits.
For an adult considering a switch from shots, the next step is a physician discussion grounded in identified triggers, formulation, safety, cost, and the likelihood of sustained adherence. At-home testing and a virtual consultation can provide an entry route when those triggers remain unclear. If drops are appropriate, home delivery and home dosing can remove much of the appointment burden after the supervised first dose. The opportunity is to choose a treatment format that makes years of immune retraining workable.
Sources
- World Allergy Organization Sublingual Immunotherapy Position Paper: 2026 update - World Allergy Organization Journal
- Frontiers
- Efficacy and safety of sublingual immunotherapy for allergic rhinitis: A network meta-analysis
- Clinical efficacy of sublingual immunotherapy for allergic rhinitis and atopic cough: 5-year real-world surveillance - ScienceDirect